Showing posts with label Recent and Future Trends in Pediatric Dentistry. Show all posts

Sunday, March 13, 2022

Lupine Publishers | Dental Home Prevalence Among Children with Medicaid in the Bronx, New York

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

The successful management of patients with cleft lip and palate deformity requires a multidisciplinary approach. Historically, cleft lip and palate care starts with treatment modality of presurgical infant orthopaedics (PSIO). However, the necessity of presurgical orthopaedics in managing the resulting orofacial deformity is the discussion to ponder upon due to the variety of methodologies available and results produced by these devices. The objectives of this paper were to review the journey of PSIO appliances so far, basic principles of PSIO treatment, the various types of techniques and the protocol followed, and to critically appraise the advantages and disadvantages of these techniques. In conclusion, we believe that PSO treatment, with its objective to approximate the segments of the cleft maxilla may reduce the intersegment space in readiness for the surgical closure of cleft sites.

Keywords: Cleft lip and palate; presurgical infant orthopaedics; PSIO

Abbreviations: PSIO: Presurgical Infant Orthopaedics; CLP: Cleft Lip and Palate; NAM: Nasoalveolar Molding; DMA: Dentomaxillary Advancement Appliance; UCLP: Unilateral Cleft Lip and Cleft Palate

Introduction

The concept of a ‘dental home’ is analogous to the American Academy of Pediatrics’ (AAP) concept of a ‘medical home.’ The national guidelines of both the AAP and the American Academy of Pediatric Dentistry recommend that children have a dental visit by 12 months of age and receive preventive care at regular intervals thereafter [1]. Dental caries remains the most common chronic disease of childhood, and early childhood caries (decay among children less than six years) disproportionately affects children of low socioeconomic status [2]. The establishment of a dental home early in a child’s life is crucial to providing continuous and family-centered preventive dental care and mitigates the consequences of poor oral health such as pain, missed school days, and emergency department visits [3]. In this study we assessed the prevalence of a dental home among children with Medicaid benefits, ages 1-17 years, presenting for their well-child medical visit. To our knowledge, we are unaware of any studies that have presented prevalence estimates for age at dental home establishment among children with Medicaid benefits.

Methods

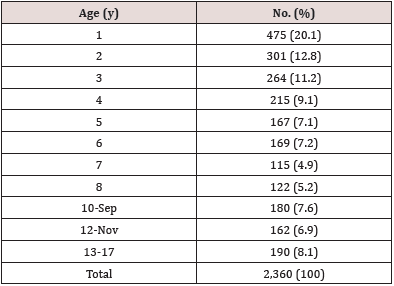
Our sample consisted of 2,360 children ages 12 months to 17 years who presented for their well-child visit at the Pediatric Primary Care Clinic at Jacobi Medical Center (JMC) in the Bronx, New York from January 2016 to June 2020. JMC is one of eleven safety net hospitals in New York City’s municipal hospital system serving a predominantly Hispanic/Latino and African American population. This observational study was approved by the Institutional Review Boards of Jacobi Medical Center and the Albert Einstein College of Medicine. As part of an interprofessional dental training program, pediatric dental residents provided dental screenings, risk assessment (AAP Oral Health Risk Assessment Tool), [4] and fluoride application in the pediatric medical clinic. The prevalence of a dental home at each age was calculated. Children making multiple visits were counted only once, resulting in a patient count rather than a visit count. All participants were Medicaid-eligible. Data analysis was conducted using Stata version 15.1 (Stata Corp) (Table 1).

Table 1:Age distribution of 2,360 children with Medicaid.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Results

Of the 2,360 children in this study, one-year-olds accounted for 20.1 percent of the sample and by this age 24.2 percent had a dental home. Children six years and younger accounted for 68 percent of the sample and by six years 49.7 percent had a dental home. Among teenagers 13-17 years old, 57 percent had an established dental home.

Discussion

The age distribution of our sample is consistent with national pediatric visit data and our analysis supports studies that have demonstrated that despite professional recommendations, significant gaps remain in the establishment of dental homes by age one for Medicaid-eligible children [5,6]. Although an upward trend is observed in the pre-school years among children with Medicaid, over 50 percent do not have a dental home by age six thereby missing a crucial opportunity for oral health education, anticipatory guidance, and preventive services during their growth and development. Among older children and adolescents, there is a plateau in establishment of a dental home at approximately 57 percent leaving many teenagers to rely on emergency departments for palliative care (Figure 1). Despite limited generalizability to a pediatric Medicaid population in the Bronx, the results of this study indicate that there is an urgent need for greater efforts and strategies to improve interprofessional education, care coordination, and dental referrals. Given that there are approximately ten well-child medical visits during the first two years of life, there is a unique opportunity for pediatric medical practitioners to provide oral health counseling and make timely referrals in order to establish a dental home by age one and end the epidemic of childhood decay among poor children.

Figure 1.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Funding/Support:

This research was supported by Health Resources and Service Administration grant D88HP28502.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, August 27, 2021

Lupine Publishers | Reconsideration of Invasive Technique for Occlusal Fissure Before Fissure Sealant

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

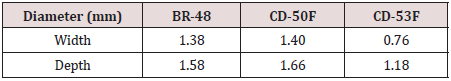
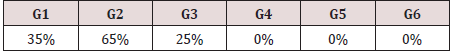
Fissure sealant is one of effectual method for prevent occlusal caries. Therefore, removing contaminated organic debris and plaque was important process to attain sufficient sealant retention. The aim of this study was revaluated the cleaning method and invasive technique to an occlusal fissure. Twenty-four teeth with deep fissure were used in this study and 15 teeth were cleaned by finger spreader, bristle brush and ultrasonic scalar, respectively. Remain 9 teeth were prepared fissure groove using three kinds of minimal intervention burs (BR-48, CD-50F and CD-53F). The ratio of remaining debris by fingers spreader, bristle brush and ultrasonic scalar were 35 %, 65%, 25% respectively. In contrast, each fissure with invasive technique was not observed residual debris. The average preparative fissure groove by BR-48, CD-50F, CD-53F were 1.38mm, 1.40mm and 0.76mm in width, and 1.58mm, 1.66mm, 1.18mm in depth, respectively. From these results, invasive technique as fissure pretreatment before acid etching might be effective to success for good fissure sealant retention for a deep and narrow fissure and a CD-53F bur was most less preparative sound enamel.

Keywords: Fissure cleaning; invasive technique; fissure sealant

Introduction

Immature permanent teeth have a risk of occurring dental caries. Especially the percentage of occlusal pit and fissure caries is over 80% of all caries in immature permanent teeth [1]and Carlos JP et al. reported that a high percentage of these occlusal lesions occurred the caries in the first 3 years after tooth eruption [2]. Dental plaques and organic debris are easy to accumulate in a pits and fissure of occlusal surface in immature young permanent teeth, and those plaque and debris were hard to remove from pit and fissure completely by ordinal cleaning method such as using low speed of rotary tooth brush. Therefore, a technique by capping of fissure with fissure sealant is widely used in ordinal dental clinic for preventing occlusal caries. However, fissure sealants are occasionally removed out partially or totally from fissure for a long term of retention. Complete or partial fissure sealant retention after 8-10 years was reported by some studies [3-5]. The main reason of them seems that fissure sealants are not able to penetrate into whole of fissure for the characteristic of narrow fissure and prevention by dental plaques remaining into a bottom of pits and fissure. Therefore, complete removal of debris and plaque are important factor for success of fissure sealant. Although conventional technique with rotary brush was commonly used by clinical dentist, there is a possibility of remaining dental plaque or organic debris in a pits and fissure with this treatment. The shape of fissure groove might influence on disturbing fissure cleaning. Because fissure are deep and narrow in immature molar teeth typically and it is hard to attach cleaning instrument to those debris and they are staying in the bottom of fissure for long period Moreover deep and narrow shape of fissure is disadvantage for penetrating of fissure sealant into whole of fissure groove. Therefore some researchers insist that invasive technique as enamel pre-treatment by fissure bur [6-9], air abrasion [10,11] or laser [12,13] before enamel etching and fissure sealing are necessary to success of cleaning of pits and fissure and penetration of fissure sealant sufficiently. However, these invasive techniques are not widely acceptable for young teeth treatment and there has still discussed whether invasive pre-treatment is necessary for fissure sealants or not [14-17]. Therefore, this study is investigated that the debris removing ability from noninvasive pit and fissure were using several kinds of cleaning methods such as conventional rotary brush, ultrasonic scalar, chemically agent. Furthermore, invasive techniques as a fissure pre-treatment were also investigated using several minimal intervention burs.

Materials and Methods

Sample corrected and preparation

Twenty-four extracted human permanent molar and wisdom teeth with deep pit and fissure were used in this study. Following an approval of use for this study by the patients, those teeth had checked their depth of fissure by dental photography and adapted similar condition of fissure were used in this study. Furthermore, they had no caries in occlusal surface. Before research, all teeth were cleaned by brushed and washed with distilled water and stored at room temperature.

Application of artificial organic debris into fissure groove

To specific valuation of removing debris ability, each fissure of all experimental teeth was filled with artificial organic debris. The organic debris was prepared according to a previous report [18]. It contained 20% of Liquitex (Liquitex Co., USA), 30% of Starch gruel (Fueki-ko, Fueki Co., Yao, Japan), 30% of Poster color (Sakura Co., Osaka, Japan), and finally 20% of solid food fragments for rats (MR-stock, Nihon-Nosan Co., Yokohama, Japan) originally used for animal feed. All ingredients were mixed together to simulate a clinical debris condition. All specimens were then stored in a moist chamber until start study.

Group classification

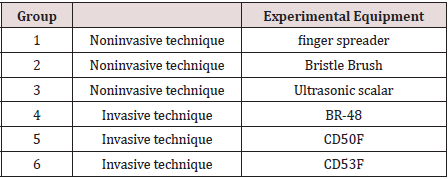
All specimens were classified into 6 groups at randomly according to the difference of cleaning method or fissure pretreated burs. Each 5 teeth were elected in group 1 to group 3 respectively (15 teeth) and those teeth were evaluated several cleaning methods without fissure invasive technique. Group1 was cleaned fissure by hand instrument (finger spreader). Group 2 was used bristle brush to fissure cleaning. Group3 was performed fissure cleaning by ultrasonic scalar. Remaining 9 teeth were divided into 3 groups (Group4 to 6) in each 3 teeth. These three groups were applied invasive technique using several types of fissure preparative burs. The detail of this classification was shown in Table 1.

Table 1: Classification of each group.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Experimental Procedure for noninvasive fissure

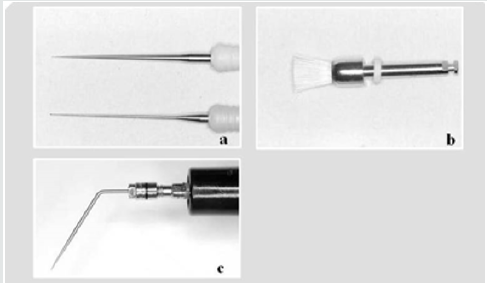
In Group 1, fissures were cleaned with finger spreader (Mani Inc Tochigi, Japan). The fissures were gently excavated with a 15- size flare finger spreader using a vibratory motion and rinsed with water spray. This process was continued until the debris was removed completely from the fissure groove (Figure 1a). In Group 2, fissures were cleaned by pointed bristle brush (Merssage brush CA, YDM Co, Tokyo, Japan) with water spray. Bristle brush was setting in a low-speed handpiece (550 cycles per minute) and leaning procedure was performed for 30 seconds. All teeth were then dried with oil-free compressed air for 20 seconds and subjected to the following investigations (Figure 1b). In Group 3, fissures were cleaned with ultrasonic scalar with thin tip (ENAC, SC point 4, OSADA Inc Tokyo, Japan) under water spray condition. Scalar head were touched and moved with the fissure groove gently and continue procedure until artificial organic debris removing (Figure 1c). Even organic debris was not removed completely, cleaning procedure using above each method was stopped within 30 seconds. Then each fissure was observed by stereomicroscope to check the ratio of residual debris.

Figure 1: The instruments for fissure cleaning.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Fissure preparation for invasive technique

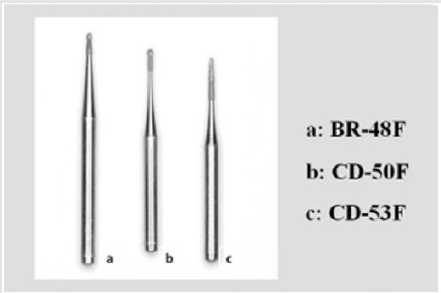
Remain 15 teeth were used for invasive technique. After each fissure groove were washed, then fissure groove was prepared by three types of diamond burs. Type 1 and type 2 were small round diamond burs (BR-48 and CD-50F). Type 3 (CD-53F) were fissure type diamond bur. These all burs were produced for Minimal Intervention (MI) and are especially designed to prepare the cavity minimally as possible. These burs were connected with high speed hand piece and keep the speed as a 3000 rpm during fissure preparing procedure (Figure 2).

Figure 2: The instruments for fissure invasive technique.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Stereoscope and SEM observation of invasive fissure

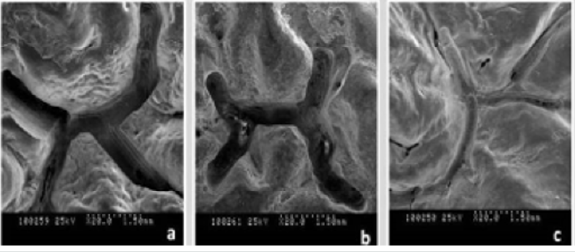
To verify the surface characteristics, each 3 teeth in group 4 and group5 (total 6 teeth) were selected randomly and fissure condition after invasive technique were examined using a stereomicroscope (SMZ-10, Nikon, Tokyo, Japan). Following stereomicroscopic observation, and then followed by scanning electron microscopic (SEM) examination. For SEM examination, specimens were dehydrated with a graded series of aqueous ethanol (70%, 80%, 90%, and 100% ethanol) for 24 hours in each solution, dried with liquid CO2 using a critical point dryer device (JCPD-3, JEOL, Tokyo, Japan), coated with a platinum layer to a thickness of 15 μm, and observed by SEM (JSM-T220A, JEOL) at 15 kV.

Results

The evaluation of each fissure preparation by several kinds rotary bur

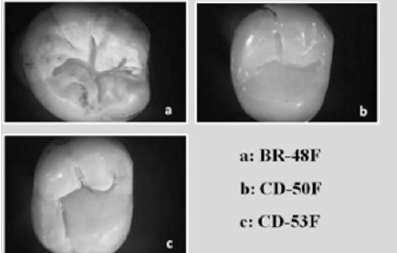
Figure 3 showed the condition of after pretreated fissures in invasive technique groups by stereoscopic observation. There was not revealed an abnormality mentioned such as a tooth fracture, tooth crack in all teeth. Scanning electric microscopic observation indicated that the pretreated fissure by the bur of CD-53F made most shallow and narrow fissure shape in three kind’s diamond burs (Figure 4). The width of invasive fissure of BR-48F, CD-50F, CD-53F were 1.38mm, 1.40mm, 0.76mm respectively. The average of depth of invasive fissure of BR-48F, CD-50F and CD-53F were 1.58mm, 1.66mm, 1.18mm respectively. Total results by fissure preparation by each diamond bur indicate in Table 2. The ratio of residual debris by each cleaning method both noninvasive fissures and invasive fissures. In the groups of normal fissures showed 25 % of debris was residue in ultrasonic scalar groups. In contrast, 35% and 65 % debris were not removed out from fissure by finger spreader and bristle brush, respectively. In 3 gropes with invasive technique to fissure, all debris was removed completely from fissures (Table 3).

Figure 3: Stereo-scope observation of fissure groove after invasive technique.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 4: SEM observation of fissure groove after invasive technique.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Table 2:The mean width and depth of each fissure groove after invasive technique.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Table 3: The ratio of residual debris by each cleaning method.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion

To attain fissure sealant, penetrate into pit and fissure completely, the process of fissure cleaning that cause free of gross plaque and debris is important key for success of fissure sealant application. This study demonstrated that several fissure cleaning techniques using finger spreader, bristle brush and ultrasonic scalar, had not success of dental organic debris removing completely in non-inversed fissure. Remaining organic debris was mainly present on the deep narrow fissure wall and bottom of the fissure groove. These results supported that previous several similar researches that compared with both bristle brush cleaning and mechanical fissure preparative cleaning. They suggested that remaining debris and pellicle were not removed from the bases of fissures by routine cleaning and etching procedures [19-21]. Therefore the reason of remaining debris of noninvasive fissure groups in this study should be the entrance to shallow and wide groove of fissure were easy to remove debris by ordinal cleaning instruments, conversely the deep fissure wall and bottom of fissure groove were not able to attack by cleaning instrument directly. Thereby many organic debris were not removing from fissure and remaining deep side fissure wall and bottom of groove even carried out several fissure cleaning techniques using finger spreader, rotary bristle brush and ultrasonic scalar. Many cases of these phenomenon were occurred by not only relate fissure depth, but also fissure width.

These types of fissure were inhibiting fissure cleaning effectiveness, and it cause insufficient etching agent and sealant penetration, and consequently reducing adaptation ability and easy to lack of retention of sealant are occurred. From this evidence, invasive technique as a fissure pre-treatment was effectiveness to both fissure cleaning and sealant penetration. Many researchers proposed that mechanical invasive technique has good advantage for fissure sealant retention [22,23]. The result of several in vitro studies on the invasive technique with mechanical preparation has indicated that the risk of microleakage is reduced when the fissure is preventively enlarged with rotating burs [24-26]. Shapira and Eidelman have shown higher retention rate in vivo with the use of a #1 round steel bur at low speed after 6 year, compared to non-mechanically prepared fissures [27,28]. Lygidakis et al. suggested their clinical study in observed for four years that the mechanical preparation of occlusal surface offer sealant retention [29]. Even these studies have demonstrated, still several researchers insist that invasive techniques were not necessary for fissure sealant application. Blackwood JA et al. reported that there was no significant difference in microleakage between the fissure cleaning with traditional pumice prophylaxis technique, fissure invasive technique and air abrasion technique [30]. However, its studies were evaluated by microleakage test using thermal cycling procedure within dwelling 500 cycles. Previous Yamada et al compared sealing ability of fissure sealant both Carisolv-and bristle brush-treated using microleakage test with 400 cycles thermal cycling [18]. Their result demonstrated that the fissure treated with bristle brush showed remaining organic materials in the bottom of groove. However, the results of microleakage tests were not specific difference both the group of removing debris completely and the group of remaining debris in bottom of the fissure.

They discussed the possibility of that the fissure sealant may have maintained a high sealing effectiveness to the marginal side wall even debris was not removed and remaining on the deep side wall in the fissure during microleakage test procedure. Therefore, microleakage test may not be a reliable evidence for the decision whether fissure pretreatment before etching and fissure sealant application is necessary or not. Accordingly sealing force of sealant was significantly reduce according passage of time and this situation might has a possibility of causing occlusal caries when it is occurred the detach or fracture of fissure sealant, and the debris which are contaminate several bacteria penetrate into bottom of the fissure. Although invasive technique is a good method for sealant retention, this technique should not necessary to transact for all pit and fissure. It must be selected for only hardness to debris remove completely by ordinal technique such as bristle brush and prophylaxis paste and prepared for only broad narrow fissure sharp fissures. De Craene et al. has also similar suggestion, they proposed that in a tooth with open fissures, not suspected of being carious, a prophylactic treatment for non-invasive pit-and-fissure sealing technique should be chosen, by contrast in case of deep and narrow fissures that are discolored and suspected of being carious, the invasive pit-and-fissure sealing technique should be chosen [22]. Welbury et al. reported that purposeful invasive technique just to widen the base of a fissure in a sound tooth is an invasive technique, which disturbs the equilibrium of the fissure system and exposes a child unnecessarily to the use of a handpiece or air abrasion [30]. Therefore, they insisted that invasive technique for occlusal fissures was not necessary and undesirable method. To resolve this doubtful problem, invasive technique must be performed most minimal preparation as possible.

This study was also investigated the invasive technique, then evaluated the instruments for fissure pretreatment both fissure type and round head diamond point bur which were produced for minimal intervention. Present results demonstrated that round head diamond point bur made causing unacceptable width and depth fissure sharp, because it seems round head diamond bur was smoothly moving and control was not easy to keep a fissure external form consequently fissures became more wide and deeper than what was assumed. Conversely, fissure type of diamond bur caused minimal fissure groove and it might be acceptable depth and width of them. This research proposed that CD53F fissure head diamond bur that was used in this study may good candidate for fissure preparation instrument and Garcia-Goddy et al. also recommended fissure type diamond point bur (Sorensen bur) [7]. From this result and previous those results, the fissure type diamond point may most acceptably instrument for invasive technique. The results of present study strongly suggested that the important factor for success of fissure sealant should select a case of proper fissure whether invasive technique is necessary or not. In case of performed invasive technique to immature occlusal fissure, minimal preparation of fissure pre-treatment is the key for safety and sufficiently good retention of fissure sealant.

Conflicts of Interest

There are no conflicts of interest.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Saturday, August 14, 2021

Lupine Publishers | Maxillofacial Prosthetics

 Lupine Publishers | Journal of Pediatric Dentistry


Mini Review

Overview

A prosthesis can be defined as- “An artificial replacement of part of the human anatomy restoring form, function, and esthetics”. Patients who have suffered maxillofacial impairment exhibit a compromised appearance making them incapable of leading a normal life. Such patients experience a change in societal acceptance that greatly affects their mental health, and often their expectation to return to a normal life crumbles. With sophistication in plastic surgery, aesthetic corrections of such defects is possible, but, if surgery is contraindicated or the defect is so extensive that full closure is not possible or if the patient is unwilling to expose him/herself to surgery, maxillofacial prosthetics appear to be a viable option.

What is maxillofacial prosthetics?

Maxillofacial prosthetics is a branch of dentistry that deals with congenital and acquired defects of the head and neck. Maxillofacial prosthetics integrates parts of multiple disciplines including head and neck oncology, congenital malformation, plastic surgery, speech, and other related disciplines. With recent advancements in prosthetic materials, coloring techniques and retentive mechanisms, a life like prosthesis can be given. The biggest impact of such prostheses is not only on the appearance but majorly on the mental health of the patient. The main objective is not only rehabilitation of the defect but also restoring confidence and improving quality of life of the patient.

Objectives

The objectives of maxillofacial prosthetics includes the following important objectives:
a) Re-establishment of esthetics or cosmetic appearance of patient.
b) Re-establishment of function.
c) Protection of tissue.
d) Therapeutics or healing effect.
e) Psychological therapy.

Types of maxillofacial prostheses

Extra oral Prostheses:

a) Ocular Prosthesis: Replaces Eye
b) Orbital Prosthesis: Replaces Eye and surrounding tissues
c) Auricular Prosthesis: Replace Ear
d) Nasal Prosthesis: Replaces Nose
e) Midfacial Prosthesis: Replaces part of the face which may involve more than One structure.
f) Somatic Prosthesis: Replaces a body part like fingers, hands, etc.
g) Radiation Shield: Worn during radiation therapy for protection of normal tissues.

Intraoral Prostheses

a) Surgical Obturator Prosthesis: Covers palate after partial or total loss of the maxilla (upper jaw). This is used after surgery to provide closure.
b) Interim and Definitive Obturator: Covers palate after partial or total loss of maxilla or due to cleft palate. It restores teeth and gums and has an extension which closes the defect or hole for swallowing, eating, chewing, and speaking.
c) Palatal Lift Prosthesis: Helps soft palate assume correct position for speech.
d) Palatal Augmentation (Drop) Prosthesis: Alters palate prosthetically for speech.
e) Mandibular Resection Prosthesis: Replaces portion of the jaw that has been lost and restores gums and teeth.

Materials Used

a) Acrylic resin.
b) Acrylic polymer.
c) Pvc- hard, clear resin, flexible, odorless and tasteless.
d) Chlorinated polyethylene- thermoplastic elastomer
substitute for silicone.
e) Silicone- most successful.
f) Polyphosphazenes.

Ideal Properties of the Material

a) High tear strength
b) Biocompatible
c) High edge strength
d) Long working time
e) Reusable mould
f) Non allergic
g) Softness and elongation
h) Translucent

Conclusion

The rehabilitation of intraoral and extra oral defects and reestablishment of function is a challenging aspect of maxillofacial prosthodontics. It requires continuing practice of the art to gain confidence and expertise. The goals of the surgeon and prosthetic specialist regarding rehabilitation of the patient are closely allied. The maxillofacial prosthodontist should always try to provide the comprehensive and thorough treatment. Sophistication in the prosthetic reconstruction of structural and functional defects improves the final results, if carefully planned, unbiased rehabilitation regimens are established. It is a basic right to look human.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, June 18, 2021

Lupine Publishers | Hemoglobin Genotype Polymorphism in Gravidas Women Attending Federal Medical Center Yola, Nigeria

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Background/Objective: Hemoglobin is the iron-containing oxygen-transport metalloprotein in our red blood cells, hemoglobin is made up of globin chains which are encoded by their respective genes located on chromosome 11 and16 with several alleles. Many of these alleles suffer point mutations in the DNA sequence that lead to single amino acid substitutions in the globin moiety, resulting in the production of abnormal hemoglobin polymorphism and which are associated with a wide range of moderate to severe hemolytic anemia in pregnant women. Therefore, this study aims to examine hemoglobin genotype polymorphism among gravidas women in Yola.

Materials/Methods: 904 pregnant (i.e. gravida) women with age range of 18 to 41years in the antenatal ward of the hospital participated in this study and 2mls of venous blood were aseptically collected from each participant into EDTA vacutainer. The hemoglobin genotype was determined within 5hours of blood collection using Helena electrophoresis tank.

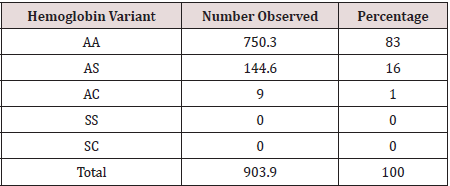
Results: 750.3(83%) of women had hemoglobin genotype of AA while 144.6(16%) women had hemoglobin genotype of AS. In addition, hemoglobin genotype AC was seen in 9(1%) of the gravida’s women while hemoglobin genotype SS and SC was not seen in this group of women within the study period.

Conclusion: Gene frequencies with regard to the hemoglobin genotype polymorphism in gravidas women has shown a general formula of AA > AS > AC indicating high prevalence of AA over AS and AC in Federal Medical Center Yola Nigeria.

Keywords:Hemoglobin polymorphism; gravidas women

Introduction

Hemoglobin is the iron-containing oxygen-transport metalloprotein in red blood cells of humans and most vertebrates. Hemoglobin in our blood carries oxygen from respiratory organs to the rest of the body, where it releases the oxygen to metabolize nutrients to generate energy that powers our body’s physiology and collects the resultant carbon dioxide back to respiratory organs to be expelled from the body. Hemoglobin is made up of heme, which is the iron-containing portion, and globin chains, which are proteins and the globin protein consists of chains of amino acids. There are several different types of globin chains, such as: alpha, beta, delta, and gamma. Hemoglobin Polymorphism in this study refers to the occurrence of variety of hemoglobin types in pregnant (i.e. gravidas) women. Hemoglobin types include:
a) Hemoglobin A (Hb A) which makes up about 95%-98% of hemoglobin found in adults; it contains two alpha (α) chains and two beta (β) protein chains[1].
b) Hemoglobin S (HbS) which is an abnormal hemoglobin with a single nucleotide substitution (GTG for GAG) in the gene for beta globin on short arm of chromosome 11, resulting in the replacement of a glutamic acid residue with valine at the sixth position of both (i.e. homozygous state) or single (i.e. heterozygous state) globin chain[2].
Hemoglobin C (HbC) is also an abnormal hemoglobin similar to HbS but in HbC, lysine replaces glutamic in the globin chain. Deoxygenation of either HbS or HbC exposes valine or lysine residue on the surface of the molecule, which forms hydrophobic interactions with adjacent chains, the resulting polymers align into bundles, causing distortion of the RBC into a crescent or sickle shape, consequently, reduces flexibility and increase deformability, which hinders passage of the cell through narrow blood vessels[3] resulting in sickle cell episodes. Sickle cell disorders include the homozygous state for Hemoglobin S, or sickle cell anemia (SS), the heterozygous state for Hemoglobin S or the sickle cell trait (AS), and the compound heterozygote state of Hemoglobin S together with other hemoglobin variants such as C or D can result in hemoglobin AC[3].The globin chains are encoded by their respective genes located on chromosome 11 and chromosome 16 and are both known to have several alleles[4].Many of these alleles suffer point mutations in the DNA sequence that lead to single amino acid substitutions in the globin moiety, resulting in the production of hemoglobin polymorphism. The abnormal hemoglobin genotype occurs when an affected individual inherits mutated globin gene(s) such as hemoglobin S, C, D, and E from both parents. Abnormal hemoglobin genotypes are inherited in an autosomal codominant fashion and occur by different combinations[5]. Several abnormal hemoglobin genotypes have been discovered but the most commonly encountered abnormal hemoglobin genotypes among Nigerians include AS, AC, SC, and SS[5].It has been reported that abnormal hemoglobin genotypes have been associated with a wide range of moderate to severe hemolytic anemia, leading to a high degree of morbidity and mortality among affected individuals as well as susceptibility to renal medullary carcinoma[6]in addition, World Health Organization ranked Nigeria as first in terms of high prevalence of infants born with abnormal hemoglobin genotype[7]. Therefore, this study aims to examine hemoglobin genotype polymorphism among gravidas women in Yola in other to elucidate the risk of giving birth to children with abnormal hemoglobin as well as risk of developing hemolytic anemia during gestation period in this locality.

Materials and Method

This retrospective and descriptive study was carried out at the hematology department of Federal Medical Center Yola in Adamawa State, Northeastern Nigeria. 904 pregnant (i.e. gravida) women with age range of 18 to 41years in the antenatal ward of the hospital participated in this study.

Statistical analysis

Statistical analysis was performed using SPSS computer software version 20.0 (IBM Chicago, IL, USA). Descriptive values were given as mean and standard error of mean. Categorical variables were expressed as the number of cases and the percentage value.

Sample collection and analysis

2mls of venous blood were aseptically collected from each participant into a tripotassium Ethylenediaminetetraacetic acid (K3 EDTA) anticoagulant vacutainer. The hemoglobin genotype was determined within 5hours of blood collection as followsa portion of the blood was put in a clean khan tube and washed 3 times with normal saline (0.85% sodium chloride). Distilled water was added to the washed red cell in ratio of 1:4 to lyse the blood sample. The lysed samples were applied on Helena cellulose acetate paper using the Helena plate and applicator, and the paper was placed in the Helena electrophoresis tank (Consort) containing a commercially prepared Tris-EDTA-Borate buffer, the pH of the buffer is 8.6. The electrophoretic separation was allowed at room temperature for 3minutes at 220V. A commercially prepared Helena known hemoglobin were run as controls along with the test, and the results were read immediately after the end of the test time.

Results

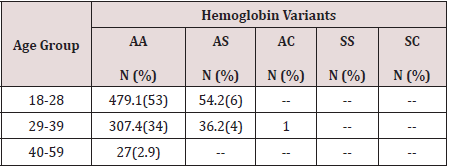
Hemoglobin genotype polymorphism in gravidas women have been analyzed and 750.3(83%) of the women had hemoglobin genotype of AA while 144.6(16%) women had hemoglobin genotype of AS. In addition, hemoglobin genotype AC was seen in 9(1%) of the gravidas women attending the antenatal clinic of federal medical center Yola as shown in Table 1.Age distribution shows that, 479(53%) and 54.2(6%) of hemoglobin genotype AA and AS respectively was seen in women within the age of 18 to 28years while 307.4(34%) of the hemoglobin genotype AA and 36.2(4%) of hemoglobin AS was observed in women within the age range of 29 to 39years. 1% of hemoglobin AC occurred in women within the age of 29 to 39years. In addition, among women at the age of 40 to 59years, 27(2.9%) was observed at P<0.05 as shown in Table 2. None of the gravidas women had hemoglobin SS or SC.

Table 1: Hemoglobin variants of gravidas women.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Table 2: Hemoglobin variants per age group of gravidas women.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion

The analysis of hemoglobin polymorphism among pregnant women in Federal Center Yola revealed that gene frequencies with respect to the hemoglobin genotype polymorphism in gravidas women has shown a general formula of AA > AS > AC indicating high prevalence of AA over AS while AC genotype was the least of the hemoglobin genotype observed in this study. This result is in agreement with the earlier report by Medugu et al.[8] In addition, 83% of the women had hemoglobin genotype AA indicating that these women had normal allele of hemoglobin A in a homozygous state while 16% of women had hemoglobin genotype AS to reflect the presence of hemoglobin A (HbA) and abnormal hemoglobin S (HbS) in a heterozygous state and inherits one normal allele and one abnormal allele encoding hemoglobin S (hemoglobin genotype AS). Hemoglobin genotype AS is also called sickle cell trait which is generally regarded as benign condition but this condition have been reported to cause medical complications in exercise, muscle contraction or dehydrated state[9] and by consequence, 16% of pregnant women in this center may be at risk of anemia hence women with hemoglobin genotype of AS may require additional medical attention during vaginal child birth which usually involves levels of muscular contractions. Furthermore, 1% of women had hemoglobin genotype AC and none of the women had genotype SS or SC and this low level of homozygous state of abnormal hemoglobin may be due to high level of medical education among couples or/ and that women with homozygous state of abnormal hemoglobin may be unable to keep pregnancy hence their absence in this study

Conclusion

Gene frequencies with respect to the hemoglobin genotype polymorphism in gravidas women has shown a general formula of AA > AS > AC indicating high prevalence of AA over AS and AC in Federal Medical Center Yola Nigeria.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Saturday, May 15, 2021

Lupine Publishers | An Assessment of Emergency Care Following Tooth Avulsion Among A Selected Population of Nigerian School Children

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Aim: To assess the knowledge of school children on the first aid administered after traumatic tooth avulsion.

Methods: A structured questionnaire was used to obtain information from children of six primary and six secondary schools in Port Harcourt, Nigeria. Information elicited included respondents’ socio-demographics, exposure to dental trauma and knowledge on emergency care for tooth avulsion. Data collected was analysed using SPSS Version 22 and level of significance was set at p <0.05.

Results:There were 411pupils; 194 males and 217 females with a mean age of 12.5 (±2.6) years. One hundred and eighty-three (44.5%) had previous dental injuries. Three hundred and twenty-three (78.6%) would seek treatment in dental clinic after tooth avulsion. Only 16 (3.9%) would replace the tooth in its socket, 160 (38.9%) would take it to the dental clinic and 192 (46.7%) will throw the tooth on a roof top. Only 164 (39.9%) would seek immediate treatment. Twenty-two (5.4%) will use milk as storage/ transport media. There were statistically significant differences between
a) The males and females in their time for seeking treatment (p=0.01).
b) The public and private school pupils on where to go for treatment (p=0.013) and transport media use (p=0.00).
c) The primary and secondary school pupils on replantation of avulsed tooth (p=0.03) and transport media use (p=0.00).

Discussion: Although majority knew who a dentist is, their knowledge of emergency care when avulsion occurs is low; they require oral health education to bridge the gap in their knowledge.

Keywords:Tooth avulsion; traumatic dental injuries; emergency care; Nigerian school children; tooth replantation; transport media

Introduction

The school is an educational institution for learning both within [1] and outside [2] the classrooms under the guidance of teachers [3]. However, recreation and sport activities [2-4] in schools when unsupervised may predispose school children to traumatic dental injuries (TDI). Such injuries occur more among males than females and more commonly in urban children than rural children [5-8]. Sixty percent of TDI have been reported to occur during sporting activities among school aged children [9,10]. Of these, tooth avulsion; the complete displacement of the tooth out of the alveolar socket, is the most severe type of TDI and it occurs in both the primary and permanent dentitions [11]. In the permanent dentition, it occurs commonly among children aged between 6-12 years, [5,8,11,12] during the period in the tooth eruption cycle when root formation is incomplete and the periodontal ligament surrounding erupting teeth are loosely structured and provide very minimal resistance to an extrusive force. Tooth avulsion has an incidence of between 0.5 to 16% [8-14] among children and an incidence of 20.8% was reported among Nigerian adolescents [15].
Tooth loss, as a result of trauma, in addition to being distressing has both functional and psychosocial consequences in the permanent dentition [9,11,16]. First aid carried out minimizes the negative emotional/social consequences and ensuing cost of treatment that may result from premature tooth loss. Timely intervention at the site of the accident and immediate presentation to a dental clinic for professional care would result in a favourable outcome [7,10,16]. Replantation is the treatment option for avulsed permanent teeth and the treatment outcome is dependent on prompt and appropriate intervention at the site of the accident [3,17]. Other factors include short extra oral time, suitable transport media, immaturity of the root apex and patients’ general health [16,18,19]. The first aid carried out at the time of injury includes replacing the tooth within the alveolar socket and immediate referral to the dental clinic [8,13] for replantation procedure. However, if the tooth cannot be replaced into its original position, a suitable storage and transport medium would help maintain the viability of the periodontal ligament cells while seeking prompt professional attention in the dental clinic. The transport and storage media include Hanks Balanced Salt Solution (HBSS), Eagle’s medium, Normal saline, Via span, propolis, milk and coconut water [13,18,19]. The most recommended medium based on maintenance of PDL cell viability, availability, low cost and long shelf life is milk as reported in the reviews by Adnan et al. [18] and Udoye et al. [19]. Parents, teachers and students, especially, are almost always present where these injuries occur and need to be knowledgeable on what to do immediately it occurs. The knowledge of parents, [17,20] school teachers [3,9,10,20-23] and students [24,25] has been assessed in several studies both within and outside Nigeria. Most of these showed a poor awareness and low knowledge of first aid measures following tooth avulsion. Though the knowledge of students has been conducted in a study in Nigeria, it was done over a decade ago in another geopolitical region [24]. The aim of this study was to assess the level of knowledge of first aid administered following tooth avulsion among school children in the South-South geopolitical region in Nigeria.

Materials and Methods

Ethical clearance was obtained from the Research and Ethics Committee of the University of Port Harcourt Teaching Hospital. Consent was sought and obtained from the State Universal Basic Education Board and the proprietors of the private schools. Consent and assent were sought from the head teachers and pupils after being assured of confidentiality, respectively. Children aged 8 to 15 years were selected from six (three public and three private) primary and six (three public and three private) secondary schools using a multistage sampling technique. A structured questionnaire [24] was used to obtain information from each of the children. The information elicited were the socio-demographics such as age as at the last birthday and sex, other information were experience of exposure to dental trauma, response to past traumatic injuries, knowledge of the emergency treatment with particular focus on tooth avulsion and knowledge on the process of replantation. The information collected was entered into data spreadsheet and analyzed using the IBM Statistical Package for Social Sciences (SPSS) software, Version 22.0 (SPSS Inc., Chicago, IL, USA). Descriptive summary statistics was obtained for demographic variables and knowledge of emergency care. Pearson’s chi square was used to assess the differences in knowledge between groups and statistical significance was set at p<0.05.

Results

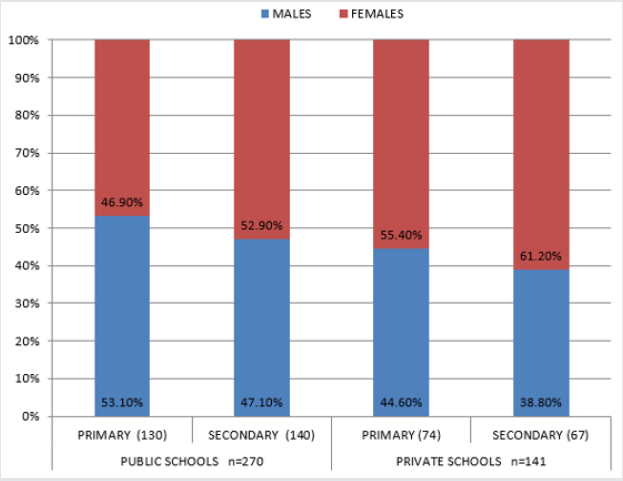
Figure 1: The distribution of the school pupils according to the type of schools, level of education and gender.

Lupinepublishers-openaccess-pediatric-dentistry-journal

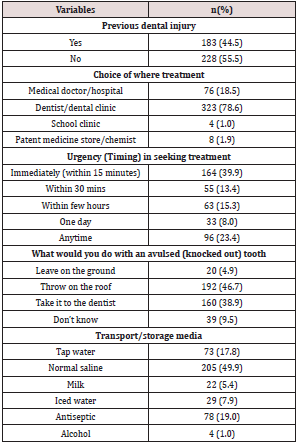
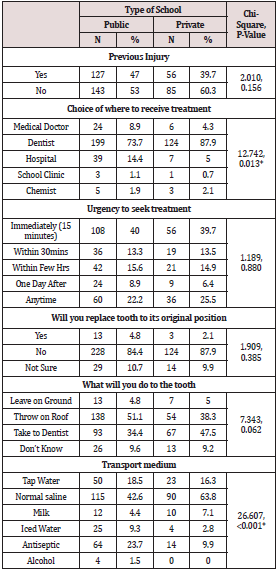
Four hundred and eleven students comprising 194 males and 217 females with a mean age of 12.5 (+2.6) participated in this study. Two hundred and four (49.6%) primary and 207 (50.4%) secondary school pupils participated in the study; 270 (65.7%) attended public schools while 141 (34.3%) attended private schools. Details in Figure 1. One hundred and eighty-three (44.5%) had history of previous dental injuries. Their responses to the questions on their knowledge of avulsion revealed that 323 (78.6%) would go to a dentist if they had tooth avulsion, 76 (18.5%) would see a medical doctor and 4 (1%) would go to the school clinic. Only 16 (3.9%) would replace the tooth in its socket. Although 164 (39.9%) would seek immediate treatment, 160 (38.9%) would take the tooth to the dentist. Two hundred and five (49.9%) would use normal saline as transport medium and only 22 (5.4%) would use milk. When avulsion occurs, 192 (46.7%) would throw it on roof top, while 160 (38.9%) would take the tooth to the dental clinic. Details in Table 1.

Table 1: The knowledge of the school pupils on traumatic dental emergencies (tooth avulsion).

Lupinepublishers-openaccess-pediatric-dentistry-journal

Gender of the subjects

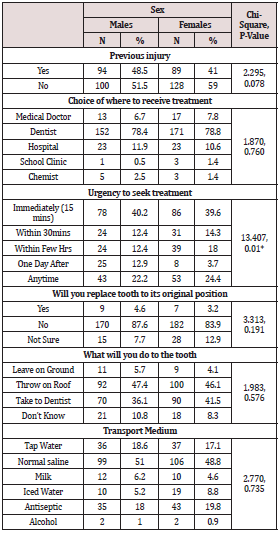
When the gender was considered equal proportion of males and females would seek treatment from a dental clinic (78%) and immediate treatment within 15 minutes (40%). Though 40% of males and females would seek treatment within 15 minutes of the injury, there were statistically significant differences between the males and females (p=0.01) in their timing for seeking treatment (Table 2).

Table 2: The relationship between the Gender and knowledge to the process of tooth replantation.

Lupinepublishers-openaccess-pediatric-dentistry-journal

*p<0.05 is statistically significant

Private and public schools

Following avulsion, 4.8%public and 2.1%private school pupils would attempt replacing the tooth within the tooth socket at the site of injury. Three hundred and twenty-three (78.6%) would go to a dental clinic for treatment, however only 164 (39.9%) would seek dental treatment immediately after the injury. More (51.1%) public school pupils compared to 38%private pupils had cultural beliefs on throwing an avulsed tooth on roof tops (p=0.06). Twelve (4.4%) and 10 (7.1%) public and private school pupils, respectively would use milk as a transport medium while 63.8% private as against 42.6% public school pupils preferred normal saline as transport medium. There were statistically significant differences between the public and private school pupils on where to go for treatment (p=0.013) and transport media (p=0.00) following avulsion (Table 3).

Table 3: The relationship between the pupil’s school type and the knowledge of the process of tooth replantation.

Lupinepublishers-openaccess-pediatric-dentistry-journal

*p<0.05 is statistically significant

Level of education

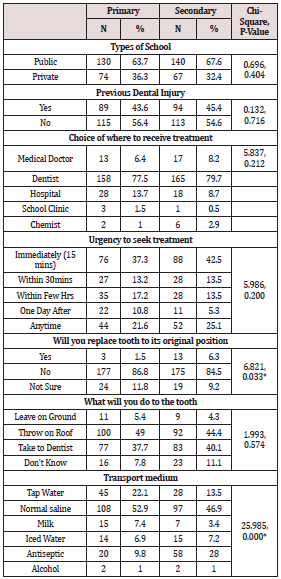
Table 4 shows that 52.9% of primary school pupils and 44.9% secondary school pupils preferred normal saline while 7.4% of primary school pupils preferred milk compared to 3.4% secondary school pupils. There were statistically significant differences between the primary and secondary school pupils on replacing the avulsed tooth back to the sockets (p=0.03), transport media (p=0.00).

Table 4: The association between the type of school, knowledge of emergency dental care and the level of education of the pupils.

Lupinepublishers-openaccess-pediatric-dentistry-journal

*p<0.05 is statistically significant

Discussion

Tooth avulsion is known to commonly occur among children in the mixed dentition phase hence the sample for this study was taken from among the school children. Though school children have teachers in the school premises, sometimes other pupils are the ones present when tooth avulsion occurs. The prognosis of treated avulsed tooth is dependent on prompt treatment which relies greatly on what is done at the site of the accident. Appropriate transport and storage media within the recommended period of storage will help maintain viability of the periodontal ligament cells, thus a favourable treatment outcome [18,19]. In this study 44.5% of the children had experienced dental trauma compared to 6-12.8% reported prevalence of TDI among the school aged children [15]. A good proportion (78.6%) of the participants would choose to receive treatment in a dental clinic. This demonstrates good awareness of whom a dentist is and understanding of the role a dentist plays in the healthcare. Such knowledge may have been fostered by series of outreaches and awareness programmes previously done in most of the schools [22]. However, there was a statistically significant difference in the level of knowledge between the private and public schools (p=0.013), the private school participants seem to know better. This finding is contrary to that reported in South Western Nigeria where the children preferred going to see a medical doctor thereby showing less awareness of the dentists’ role [24].

It was observed that 53.3% would seek professional care within 30 minutes after tooth injury, 23% may not seek care based on their choice of seeking care at “anytime”. This is a concern for a condition that requires urgent care and an off shoot of poor awareness of the importance of prompt treatment following dental trauma. The first aid measures at the site of injury include replacing the tooth in its original position [3,13] or placing in a suitable transport medium [13,18,19]. Only 16 (3.9%) would replace the tooth in its original position in the socket and there was statistically significant difference between the primary and secondary school pupils (p=0.03). This value is less than the 17.8% reported in the south west Nigeria [24]. When the gender and type of schools were considered there were no statistically significant differences between the males and females (p=0.19) and schools (p=0.39). There must be an understanding of tooth anatomy and most importantly there should be a formal teaching on what to do when tooth avulsion takes place. Though the most suitable transport medium listed was milk, [18,19] a good majority preferred normal saline, probably because normal saline appears more medicinal than milk. In this study it was observed that (46.7%) school children had a strong cultural belief on what should be done to a tooth that has been avulsed. This was shown by their response that they will throw the avulsed tooth on roof tops. This belief was commoner among pupils in public schools. The finding buttresses what was reported in a similar study in another geographical location within Nigeria with a different culture [24]. This belief stems from the myth that when a lizard sees an exfoliated tooth, that the succedaneous tooth would not erupt, so to prevent this from happening, the exfoliated teeth were thrown on roof tops away from the lizards [25]. The practice of throwing on roof tops has also been observed in some Asian countries like India, China, Japan, Korea, and Vietnam, although for different reasons [26]. The implication of this, is that the avulsed permanent tooth that would have had a chance of survival from replantation procedure in the dental clinic were being thrown away.

Conclusion

Traumatic dental injuries though a common occurrence amongst these school children (44.5%), their knowledge on first aid measures administered when tooth avulsion occurs before professional intervention is low. Although the children were aware of whom to see when they have dental injuries, the children still hold on to cultural beliefs which could be detrimental to the maintenance of the integrity of the dental arch hence oral health. These gaps in knowledge on first aid following tooth avulsion should be addressed by improving oral health education on traumatic dental injuries with emphasis on emergency care of tooth avulsion in schools. The curriculum on health education in schools should include oral care during dental emergencies.

Conflict of Interest

None of the authors have any conflicts of interest that should be disclosed.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, May 7, 2021

Lupine Publishers | Periodontitis in the Developmental Age: Pathogenesis, Epidemiology, Differential Diagnosis and Treatment. A Narrative Review

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Objective: The purpose of this study is to deepen the description of aggressive periodontitis in developmental age patients going through pathogenesis, epidemiology, diagnosis, treatment and differential diagnosis.

Methods: The database searching was performed on PubMed and Scopus using the following keywords: “prepubertal periodontitis, aggressive periodontitis, periodontitis in children, periodontal disease in children and adolescents, early-onset periodontitis”. Both clinical, laboratorial and review studies were taken into consideration.

Results: Aggressive periodontitis affects a low percentage of children, and in those patients. Actinomycetemcomitans is the main bacterium identified in affected sites. Moreover, it has been found that Genetics plays a fundamental role in development and progression, which is important to distinguish the various oral manifestations excluding the possibility that they are a consequence of systemic pathologies. Although it mainly affects young patients, the treatment does not differ from that applied in adult subjects and it consists of a causal therapy, a mechanic and a pharmacological one, in particular the antibiotics associated with professional hygiene has shown very satisfactory results.

Discussion: Given the great variability of oral manifestation symptoms, there is no specific criterion for defining a high-risk group at prepubertal age, further research is needed to identify a robust set of genetic, microbiological and host factors markers that may facilitate the diagnosis of the disease.

Keywords: Aggressive periodontitis; periodontal disease; developmental age; differential diagnosis

Introduction

Periodontal disease is one of the most widespread diseases in the world and is, as a prevalence, immediately after diseases such as diabetes and hypertension [1]. Its clinical aspects have long been analyzed since it constitutes a worldwide problem. The pathology affects subjects of every race, sex and age and also some risk factors are needed in addition to the individual susceptibility for it to develop. Even today there are not enough scientific certainties to establish the behavior of periodontal disease in the age group that affects children and young adults. In any case, we proceeded through a search in the literature with the attempt to deepen its clinical aspects, etiology, diagnosis, predisposing factors and treatment. Periodontal diseases, despite being widespread especially in the adult population, are not so rare even among young people [2]. For example, gingivitis affects over 70% of children over the age of seven [3]. Bimstein in 1991 underlined the importance of prevention, early diagnosis and treatment of periodontal diseases in children and adolescents because they have a high severity and prevalence [4] and furthermore, the oral-dental incipient pathologies on small subjects can develop into periodontal diseases in adults. However, the degree of extension and destruction of periodontitis also responds to a personal predisposition to the disease. The severity index of periodontal disease can also be mediated by the presence of some systemic diseases such as hypophosphatasia or leukocyte deposition deficiency [5].

According to Lamster IB and Pagan M, the metabolic syndrome (MetS) that is a spectrum of conditions that include dysglycemia, visceral obesity, atherogenic dyslipidemia (high triglycerides and low levels of high-density lipoprotein) and hypertension are associated with periodontal disease. They believe that this relationship is the result of systemic oxidative stress and an exuberant inflammatory response. Evidence suggests that periodontal therapy may reduce serum levels of inflammatory mediators so periodontitis treatment could become part of the metabolic syndrome therapy [6]. Among the various types of periodontitis, one of the less studied ones is aggressive periodontitis. The manifestations of aggressive periodontitis in young people have many controversial sides and consequently, the present study proposes to look for some clarifications regarding the aspects of the pathology

Methods

For this narrative review, the database searching was performed on PubMed and Scopus using the following keywords: “prepubertal periodontitis, aggressive periodontitis, periodontitis in children, periodontal disease in children and adolescents, early-onset periodontitis”, the investigation then focused on evaluating the specific aspects of aggressive periodontitis in children, consequently the following words have been introduced: “epidemiology, classification, progression, treatment, diagnosis”. Clinical and laboratorial studies were taken into consideration as well as literature reviews. The last database search was performed in September 2019.

Discussion

Aggressive periodontitis

Aggressive periodontitis can occur in several forms that is linked to a few dental sites or in a generalized sense. The first form usually affects smaller subjects and is connected to lesions of the first molars or incisors or both in the presence of little plaque and tartar, and the second form concerns post-puberty subjects with more permanent teeth. Very often, if left untreated, the localized forms evolve into general forms with the risk of a total compromise of the dental apparatus. Sometimes the signs of inflammation are not so easily detectable, which is why a child or teenager on the first visit should always be subjected to a more in-depth analysis by using probes to detect probing depth and radiological investigations. There are some mechanisms that regulate evolution in the various age groups, and the different anatomies and physiologies can modify the development of periodontitis. In particular, there are many structural inequalities between adults and children. The gingiva in the young is more vascularized, has less connective tissue around the deciduous teeth, the epithelium is thinner and less keratinized, characteristics that can expose to less defense to attacks bacterial. It can be said that a child, due to its thinness of tissues, is more exposed to risk and moreover a greater vascularization allows an easier transit of inflammation mediators and bacteria [7]. The typical signs that indicate the presence of a problem and that should alarm the parents are bleeding gums during home hygiene practices, swelling, halitosis accompanied by any recessions. Evidence shows that periodontal disease may increase during adolescence due to lack of motivation to practice oral hygiene but also due to changes related to puberty. Hormones such as progesterone, estrogen and testosterone cause greater blood circulation, greater sensitivity and greater response to any irritation, the gengiva are often red and swollen. Hormones are molecules with specific regulatory abilities and have powerful effects on the main determinants of development and on the integrity of the skeletal cavity including periodontal tissues [8].

Epidemiology

A 1987 study by Sweeney [9] evaluated alveolar bone loss around primary teeth in a population of 2,264 children. Nineteen patients (0.84%) showed periodontal bone destruction around one or more primary teeth; in 2 of these patients, periodontal disease was previously identified during clinical examinations. The microbiological study also revealed a high prevalence of Actinobacillus actinomycetemcomitans and Capnocytophaga. Another study carried out by Bimstein [10] in 1994 verified the prevalence of alveolar bone loss in a group of 317 5-yearold New Zealand children. The results identified that there was a questionable bone compromise in 8.5% of the children and a defined bone loss of 2.1%. Darby et al in 2005 studied bone loss in 542 children aged between 5 and 12 years. Reading the patient’s radiographs, each interdental site was evaluated as: no bone loss and therefore distance from the amelite-cementitious junction to the alveolar ridge of less than 2 mm, questionable bone loss i.e. distance greater than 2 mm but less than 3 mm and bone loss defined or distance greater than or equal to 3 mm.
The results showed that 61 (13%) children presented sites with definite bone loss, 60 children had only a questionable bone loss, 50 children had only a defined bone loss and 21 children had both lesions. It was also found that children of Asian-Far Eastern origin had a higher percentage of sites with bone loss than children of Caucasian origin, 29.5% and 19.7%, respectively, but lower than that of children of Middle Eastern origin (35.2%). In conclusion, the present study showed that in the population studied, 26% had bone loss but 13% had more severe and defined lesions [11]. The studies described above thus show that the prevalence of periodontal disease and in particular bone loss varies from 0.84% to 13%, but in reality, the heterogeneity of such research and the lack of standardization makes it clear how the results are discordant and the prevalence remains mostly dubious.

Microbiology

There are some bacteria that mainly cause periodontal disease, and these can be transmitted within the family where the contact between subjects is very close; through the mother’s saliva, for example, children may be exposed to risk. Much attention has been paid to Actinomycetemcomitans as a species implicated in the etiology of aggressive periodontitis. Its main virulence factor is a leukotoxin capable of eliminating important cells of the immune system. Genetic analyses have identified a population structure of the clonal-type bacterium with evolutionary families corresponding to serotypes. A particular highly leukototoxic clone (JP2) of serotype b was discovered. Its characteristics are unique in fact that its increased leukototoxic activity is given by a deletion of 530 bases in the operon. The geographical mapping of the JP2 clone has revealed that its colonization mainly concerns individuals of African origin [12]. A study conducted by Burgess et al. in 2017 showed the prevalence of the highly leukotoxic JP2 sequence compared to the non-JP2 sequence of Aggregatibacter actinomycetemcomitans within a group of 180 young African Americans aged between 5 and 25 years with and without localized aggressive periodontitis (LAP).
Subgingival plaque was collected from diseased sites, i.e. from areas with probing depth greater than or equal to 5 mm that presented bleeding and from healthy sites, i.e. from areas with probing depth less than or equal to 3 mm that did not present bleeding. Overall, 90 subjects (50%) tested positive for the JP2 sequence, 50 subjects (83.33%) with aggressive periodontitis presented the sequence detected in 45 (75%) sick sites and 34 (56.67%) healthy sites [13]. Actinomycetemcomitans in general is considered an opportunistic pathogen of the oral microbiome, in fact many clonal types of the bacterium different from JP2 can be isolated from healthy subjects, however, patients who present the JP2 strain always show periodontal disease, so an etiological agent is important for aggressive periodontitis in children, adolescents and adults. In conclusion, there is a high risk for the development of the disease in individuals colonized by the JP2 clone, furthermore its transmission, as for other clonal types, occurs vertically by close contact between people, indicating that subjects of the same family may experience extrinsic routes of the subpopulation of the bacterium [12].

Genetics

Genetics plays an important role in the appearance and severity of the disease, so if a person is diagnosed with aggressive periodontitis, it is also good to investigate the other members of the family in order to cure or prevent their appearance. A 1994 study by Mary L Marazita studied evidence of autosomal dominant inheritance and specific heterogeneity in aggressive periodontitis. Analyses were conducted on 100 families, and 104 subjects were diagnosed with aggressive periodontitis. Heterogeneity tests were used to compare the parameter estimates and the conclusions obtained in the black and non-black families. The results of the segregation analysis have verified that an autosomal dominant locus is sufficient to explain the patterns of disease transmission to the whole family. In conclusion, in the present study, we saw how the disease has a chance of appearing in the same branch of descent at 70% [13]. Family aggregation of aggressive periodontitis is not an unusual discovery. The conditions of development of this pathology can be more complex than simple Mendelian syndromes. Genetic studies indicate that there are several genetic variants expressing different forms of aggressive periodontitis, but currently it is not clear how many genes may be involved in these non-syndromic forms of disease [14]. It is important to remember that family models can also indicate exposure to common environmental factors within the same family. Therefore, the behavioral components shared by the same parental group must also be considered: education, socioeconomic status, oral hygiene, possible transmission of bacteria, diseases such as diabetes and environmental characteristics such as even passive smoking influence the susceptibility of the subject as risk factors. Another decisive reason for determining whether individuals develop periodontitis appears to be regulated by the way they respond to their microflora. Genetic factors also in this case modulate the way in which individuals interact with many environmental agents, including biofilm. The mutual influence of genetic and environmental factors, and not only of genes, determines the result, lifestyle factors open the way to the development of aggressive disease [15].

Treatment

When a child is diagnosed with aggressive periodontitis, prompt action must be taken to achieve maximum reduction of periodontal microorganisms with the aim of blocking the development of a more severe clinical picture. The treatment of aggressive disease in children and adolescents does not differ from the techniques applied to adults, in fact the etiology is always known to be bacterial regardless of age group. The treatment therefore should be based on the elimination of pathogens by professional hygiene, but, in reality, in these forms of periodontal disease given the high toxicity of the microorganisms, a systemic therapy with antibiotics must be associated to resolve the picture. The goal is to create a clinical condition that favors the maintenance of the greatest number of teeth for as long as possible. The initial phase of active treatment consists of mechanical cleaning, performed with or without the use of antimicrobial drugs.

The downsizing and smoothing of the roots have proved effective in improving the clinical indices, but they do not always guarantee long-term stability, which is why systemic antibiotics as adjuvants for radicular treatment are to be administered during therapy, and they are more effective than root resizing alone with the additional application of local or antiseptic antibiotics [16].
A 2005 study by Guerrero et al. evaluated the systemic administration of amoxicillin and metronidazole in non-surgical therapy for the treatment of generalized aggressive periodontitis. Forty-one systemically healthy subjects in whom the disease was diagnosed were selected. Patients received non-surgical treatment over a 24-hour period and one half received a course of systemic antibiotic consisting of 500 mg of amoxicillin and 500 mg of metronidazole three times a day for 7 days while the other group of subjects received placebo. After two and six months, they were re-evaluated and the results were as follows: in patients on antibiotic therapy in the 7 mm pockets there was a gain of 1.4 mm and a recovery of bone equal to 1 mm in addition to the areas with depths greater than or equal to 5 mm had a probing less than or equal to 4 mm. Twenty five percent of sites in test patients had a successful improvement in clinical attack, whereas for patients treated only with placebo, the percentage of improved sites was 16% [17]. Another study by Kaner shows how the subgingival application of chlorhexidine via a controlled release device (CHX chip) does not improve the clinical outcome in generalized aggressive periodontitis. The purpose of that study is to compare whether the additional positioning of the CHX chip is as effective as the use of systemic antibiotics. A total of 36 patients were diagnosed with aggressive periodontitis, one half was treated only with slow-release chlorhexidine and the other half treated with systemic antibiotic therapy. The subjects were re-evaluated 3 and 6 months after therapy, and it was shown that the level of clinical attack, bleeding and probing depth had a significant improvement in patients receiving amoxicillin and metronidaziol compared to patients treated with the local application of antiseptics [18]. An alternative method for the decontamination of periodontal sites has been studied: photodynamic therapy. To reduce the excessive use of antibiotics, new disinfection strategies have been sought. Photodynamic therapy (PDT) or light-activated disinfection (LAD) was first tested by Oscar Raab in the early 1900s.
For years it was abandoned due to the use of antibiotics, but it has found a new application in the last decades both in the medical field and in the dental field. The photodynamic reaction takes advantage of the use of a photosensitizer (PS) and a light source calibrated to specific wavelengths in the presence of oxygen. It acts specifically against both Gram + and Gram- microorganisms without causing any damage to the host cells. The toluidine blue is very effective active against many bacteria including those involved in periodontal disease. One example is Arweiler’s [19] research in which the use of antibacterial photodynamic therapy (aPDT) was studied in addition to mechanical scaling and root planning therapy. The aim of that study was to evaluate the results following non-surgical periodontal therapy and additional use of aPDT or amoxicillin and metronidazole (AB) in patients with aggressive periodontitis. Out of 36 patients treated with antibiotic therapy or with two episodes of post-treatment photodynamic therapy, the results after six months were the following: the probing depth was found to be significantly reduced in both groups.
Despite this, the administration of amoxicillin and metronidazole produced higher improvements than the existence of photodynamic therapy, the number of pockets ≥7 mm was reduced from 141 to 3 after AB and from 137 to 45 after aPDT. Although both treatments led to statistically significant clinical improvements, AB showed a reduction in probing depth and a lower number of pockets ≥7 mm compared to aPDT. In conclusion, photodynamic therapy associated with the non-surgical periodontal therapy, despite giving favorable results, cannot be considered a definitive alternative to the systemic use of amoxicillin and metronidazole [20]. However, antibiotics must be administered during or after mechanical therapy since micro-organisms are particularly protected by biofilm in the subgingival plaque. With regard to surgical treatment in patients with aggressive periodontitis, it has been shown that it gives results comparable to non-surgical treatment provided that correct oral hygiene is maintained, that a rigorous maintenance program is followed and that risk factors are kept under editable control [18].

Differential diagnosis

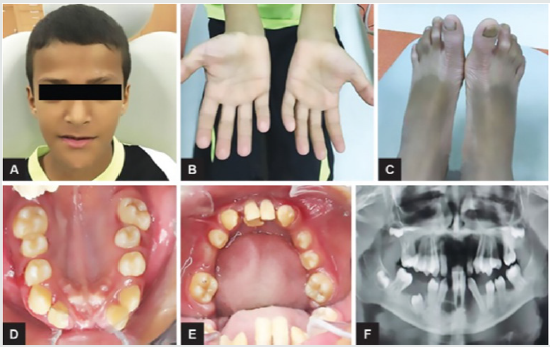
Figure 1:
Lupinepublishers-openaccess-pediatric-dentistry-journal

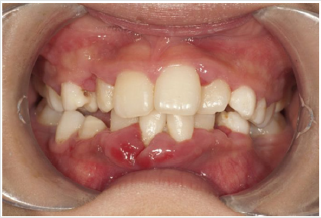
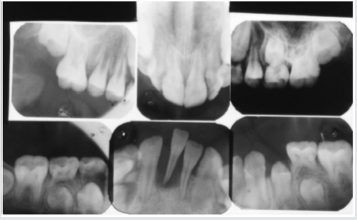
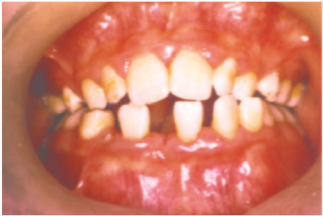
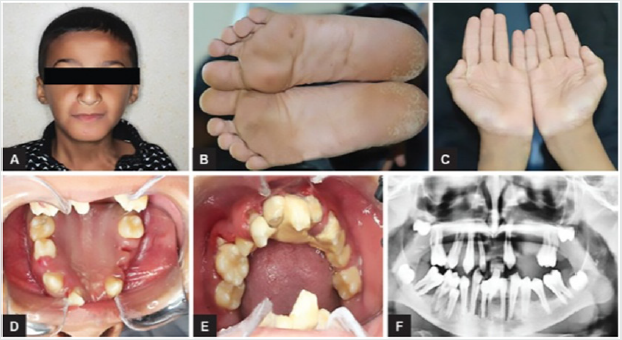
Periodontal disease is characterized by the imbalance between pathogens and host defenses leading to an inflammatory reaction around dental tissues. To diagnose aggressive periodontitis, it is necessary to investigate the health status of the subject and exclude the coexistence of systemic diseases. Some disorders can cause oral lesions clinically similar to those of aggressive periodontitis, but it is of fundamental importance to distinguish the various manifestations to make a correct diagnosis and intervene with the most appropriate treatment. Examples of significant conditions are AIDS, leukemia, diabetes or rare genetic disorders such as histiocytosis X and Papillon-Lefevre syndrome. The latter is a rare autosomal recessive disorder caused by mutations in the gene that codes for cathepsin C (dipeptidyl-peptidase I inhibitor). The syndrome is characterized by hyperkeratosis, destructive periodontitis that occurs from childhood, recurrent piogenic and systemic skin infections, susceptibility to bacterial infections and intra-cranial calcifications [21] (Figures 1&2). The prevalence is estimated to be between 1 / 250,000 and 1 / 1,000,000 subjects and is manifested in all ethnic groups. These dermatological features appear between the first year of life and 4 years and are accompanied by intraoral lesions that include gingival inflammation, mobility of the dental elements, even spontaneous bleeding and destruction of the periodontium. Patients with this syndrome show serious signs in the oral cavity until complete loss of deciduous bone, generating the normal appearance of the gum. However, with the eruption of permanent teeth, the form of aggressive periodontitis reappears. Any non-surgical but also surgical treatment is vain and almost always leads to partial or complete edentulism in the patient. The treatment is based on the intake of oral retinoids, which attenuate the palmoplantar keratoderma and slow down the lysis of the alveolar bone, and the skin lesions can also be treated with emollients in order to hydrate the affected area. Furthermore, good oral hygiene control, the use of mouthwashes and even antibiotics are recommended to slow the progression of periodontitis. Deciduous teeth or elements with excessive mobility must be extracted and eventually replaced by implants when the subject has completed growth.

Figure 2:
Lupinepublishers-openaccess-pediatric-dentistry-journal

The identification of the syndrome at an early age is something multidisciplinary that can improve the patients’ prognosis [22]. Leukemia is a malignant neoplastic disease of white blood cells and very often strikes in the pediatric age giving oral manifestations prior to systemic onset [23]. Acute lymphoblastic leukemia (ALL or ALL), specifically, develops when a cell destined to give rise to cells of the immune system turns into a tumor and starts to multiply in an uncontrolled way. Many studies show that acute lymphoblastic leukemia is the most frequent tumor in children, representing 75% of all newly diagnosed leukemias and 25% of all childhood malignancies [23]. The typical symptoms that characterize lymphoblastic leukemia are fatigue, dyspnea, fever, pallor and weight loss. Patients with this form of leukemia in the oral cavity have pale mucous membranes and an important gingival bleeding accompanied by lymphadenopathy in the head and neck region. It has been shown that sometimes the initial sign of the disease may correspond to a pericoronitis associated with a prolonged contraction of the masticatory muscles. Numerous studies have also reported a greater incidence of abnormalities in the oral cavity such as the presence of large, irregularly shaped ulcers, halitosis and a loose mucosa [24].
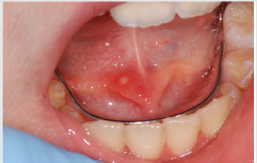
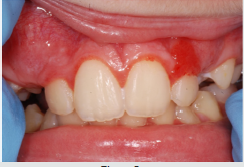
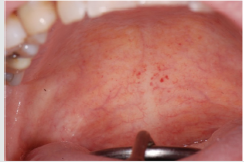
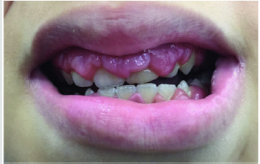
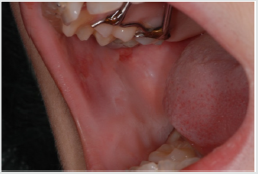
Acute myeloid leukemia (AML) is a disease that originates from the bone marrow. The disease is more common in adults over 60 years and infrequent before the age of 45. Patients with AML have symptoms related to complications related to anemia, neutropenia and thrombocytopenia, including weakness and easy fatigue, infections of varying severity, gingival bleeding, ecchymosis, epistaxis [25]. The oral examination can show pallor of the mucosa (Figure 3), ulcerations (Figure 4), spontaneous bleeding and bleeding (Figure 5) petechiae on gums, palate (Figure 6), tongue or lips, gingival hyperplasia (Figure 7) caused from leukemic infiltration. Usually the lesions of the oral cavity are the first manifestations of the disease, in particular, gingival swelling represents 5% of the early complications [26]. In leukemic patients, regardless of the form of the disease, oral manifestations occur as initial evidence or of its recurrence. Symptoms mainly include gum enlargement and bleeding, oral ulceration, petechiae, mucosal pallor and oral infections. These lesions may be the result of direct infiltration of leukemic cells or altered granulocyte function [26]. With regard to oral hygiene, patients must undergo periodic checkups and deplaquing or scaling sessions to reduce the level of inflammation of the mucous membranes, local antiseptics or antibiotics can be combined with active infections. Chemotherapy, often used in the treatment of leukemia, also has consequences on the subject that also affect the oral cavity. Often patients in therapy are predisposed to the appearance of ulcers, lesions, infections and are prone to have a partial xerostomia favoring plaque buildup.

Figure 3
Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 4:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 5:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 6:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 7:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Scurvy is another disease that manifests itself with abundant gingival bleeding and which can be confused with aggressive periodontitis. The primary cause of scurvy is the insufficient intake of vitamin C mainly due to dietary imbalances. Childhood scurvy generally appears between the sixth and twelfth year of life. The child is easily irritated without appetite and fatigued. Sufferers of this disease develop anemia, weakness, fatigue, edema in some parts of the body, muscle pain in the lower limbs and ulceration of the gums (Figure 8) [27]. It occurs later as follicular hyperkeratosis and haemorrhage of the lower limbs, as well as bleeding in other areas such as the gingiva and joints [28]. If the disease is not treated it is potentially lethal due to important bleeding that can occur in the intracranial area or, due to the poor ability of the subject to heal due to open wound infections. At the oral level, the disease manifests itself in widespread hypertrophic areas of the violet-colored mucosa, a tendency for bleeding and the formation of hematomas. In small subjects, the symptoms that appear first are the pain and swelling of the joints accompanied by gingival hypertrophy [29].

Figure 8:
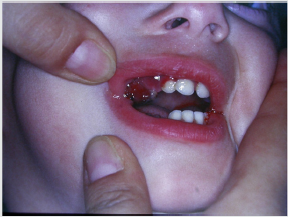
Lupinepublishers-openaccess-pediatric-dentistry-journal

Patients suffering from this pathology are administered quantities of vitamin C orally or through injections and, in a short time , all symptoms disappear [28] (Figure 9). Diabetes mellitus is a disease that can present in the oral cavity as aggressive periodontitis and be confused with this. It includes a group of chronic metabolic disorders that turn out to be an altered glucose tolerance or an altered metabolism of lipids and carbohydrates [30]. It has been shown by numerous researches that in diabetic children with poor metabolic control, there is a greater tendency for gingivitis [30]. In fact, the high levels of glucose in the blood cause changes in microcirculation, promote bacterial proliferation and interact with the response of the host. Hyperglycemia caused by diabetes mellitus alters the immune system and the increased availability of glucose in the oral cavity environment increases the proliferation of periodontopathic bacteria and causes marked oral inflammation (Figure 10). In patients with diabetes, a microangiopathy occurs and this change in the periodontium reduces the functions of the polymorphonuclear cells, the chemotaxis, the adherence, the phagocytosis, the use of oxygen and the elimination of antigens, thus favoring the progression of periodontal disease. Hyperglycemia also reduces the solubility of collagen, reduces the production of fibroblasts and causes an increase in the levels of pro-inflammatory mediators responsible for the destruction of connective tissues. Changes to collagen metabolism result in accelerated degradation of both non-mineralized connective tissue and mineralized bone.

Figure 9:
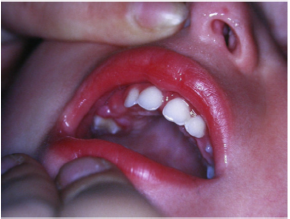
Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 10:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Even the saliva undergoes both qualitative and quantitative changes. Often in subjects with diabetes, the salivary flow is reduced leading to a further development of the bacterial species [31]. In diabetic patients, periodontal disease develops at a younger age than the healthy population and periodontal impairment usually occurs in adolescence but sometimes earlier in children with diabetes [32]. In the oral cavity, there is therefore an edematous and very inflamed gingiva, bleeding when the probe passes and bone resorption can occur especially in cases of poor metabolic control (Figure 11) [33], but in patients with a good diet with good glycemic supervision and good oral hygiene, do not show evident alteration in the mucosa (Figures 12&13). There is then a relationship between higher levels of plaque and a higher incidence of gingivitis in children with diabetes, moreover, the differences in oral microflora and the impact of metabolic control of diabetes on periodontal health have indicated a higher risk of periodontitis in children with type 1 diabetes [34]. In conclusion, when you are confronted with a child who has an oral situation of persistent inflammation, you need to perform more specific tests to understand if it is periodontitis as a manifestation of systemic pathology or aggressive periodontitis itself. The dentist or hygienist is usually the first to diagnose some diseases due to the involvement of the periodontium, and it is important to have multidisciplinary management to try to minimize the physical, psychological and social effects of the patient at an early age.

Figure 11:
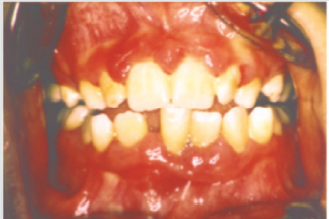
Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 12:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 13:

Lupinepublishers-openaccess-pediatric-dentistry-journal

Conclusion

In conclusion, the review of the literature shows that periodontal disease does not only affect adults but, even if less frequently, it also involves children and adolescents. The forms of aggressive disease show a family aggregation, cause an important and rapid destruction even in the absence of local irritative factors and occur in systemically healthy subjects. It has been seen that particularly virulent bacteria trigger the process of bone destruction in the disease, the main micro-organism involved is Actinomycetemcomitans, which produces powerful leucotoxins that can also severely damage the subject’s immune system cells. Some clonal types of the bacterium are very pathogenic, and JP2 is always isolated from subjects suffering from aggressive periodontitis indicating that it is an important etiological agent. Regarding the epidemiological aspects, the statistics show very variable data also depending on the country, and so far the prevalence of aggressive periodontitis is not known exactly but it can be said that it occurs mainly in subjects of African descent and in individuals who are predisposed from the genetic point of view.

To date there is no specific criterion for defining a high-risk group for prepubertal pathology, and further research is needed to identify a robust set of genetic, microbiological risk markers and host factors that favor a diagnosis of the disease in association with young people and adolescents. The identification of aggressive periodontitis can be implemented through periodontal screening associated with radiographs, and the routine use of BPE can be helpful for early diagnosis. The treatment consists of the same methods applied also to adult patients, that is to say a causal therapy, a mechanic and a pharmacological one, in particular the studies have shown that antibiotics associated with professional hygiene in patients with aggressive periodontitis give very satisfactory results. If, despite careful treatment and hygiene, a child continues to have periodontal problems, it is necessary to investigate the general health with more specific examinations. A form of periodontal injury in a young person can also be a symptom of systemic diseases that are extraneous to the parent’s awareness and early diagnosis can become vitally important. Aggressive periodontitis, although infrequent, is not to be underestimated and it is important to take children to regular checkups and scaling sessions. Preventing and diagnosing problems early is the key to success.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/


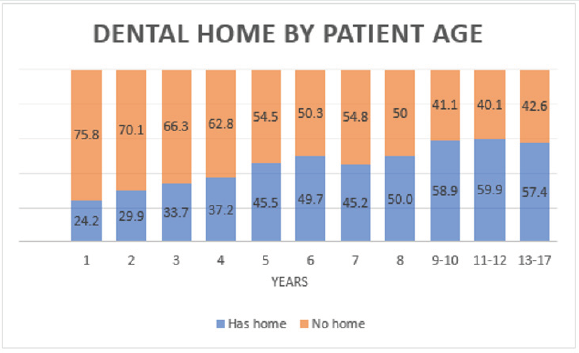
980 nm Diode Laser: A Good Choice for the Treatment of Pyogenic Granuloma

Abstract Pyogenic granuloma is a benign non/neo plastic mococutanous lesion . It is a reactional response to constant minor trauma and ca...